

Tinnitus (also called “ringing in the ears,” “phantom sound,” “buzzing,” “whistling,” or “auditory vibration”) is one of the most common symptoms encountered in practice in ENT, neurology, physical therapy, dentistry, and even psychiatry. For some patients, it is just a mildly annoying symptom, but for others, it can become a severe problem with a major impact on sleep, concentration, anxiety, and quality of life.
Innovation Medical Center is the ATM Therapy Center, with digital technology at the 2026 level, a leader in Romania in minimally invasive laser treatments, with a medical team specialized in ATM treatments. Innovation Medical Center is an associated center and European partner of Sigmund Freud University Vienna and AALZ Germany, being affiliated with ISLD, which guarantees clinical practices aligned with international academic and scientific standards in laser dentistry and ATM therapy.
Important to understand: Tinnitus is not a disease in itself, here a signal that a dysfunction has appeared somewhere along the auditory-neurological-muscular-articular chain. And one of the most subdiagnose causes this temporomandibular joint (TMJ) dysfunction.
In this article, we explain all causes of tinnitus from all relevant perspectives (ENT, neurology, dentistry/TMJ, psychology/psychiatry, rehabilitation, cardiology, imaging) and then we go into detail about the relationship between Tinnitus and TMJ with clear anatomical and functional mechanisms. Finally, we describe how we treat this condition today, in 2026, tinnitus caused by TMJ disorder through a protocol integrated into Innovation Medical Center Bucharest.
What is tinnitus (and why does it occur)?
Tinnitus is Perception of a sound without a real external source. It can be
tall (squeaking, whistling, “electronic”)
down (shiver, vibration, “motor”, “waves”)
Constant or intermittent
unilateral or bilateral
associated with ear pressure, dizziness, hearing loss, or neck/jaw pain
From a medical perspective, tinnitus can have the following causes:
ear (outer ear)
central (brain / neural pathways)
Somatosensory (ATM + cervical + muscle + fascial)
vascular-metabolic
emotional-psychological (heightened perception and autonomic nervous system stress)
1) Causes of tinnitus from an ENT perspective (inner and middle ear)
ENT is often the first specialty a patient turns to because tinnitus is perceived as an “ear problem,” and very often, there is indeed a real auditory mechanism involved.
Common ENT Causes:
Sensorineural hearing loss (including mild or “hidden” distortion, especially at high frequencies)
Acoustic trauma (loud music, club, headphones, industrial noise)
Ear infection / Eustachian tube dysfunction / Pressure
Otosclerosis
Muscle spasm in the middle ear area (sometimes with a perception of vibration)
Ménière's disease
The ENT specialist plays a crucial role in ruling out emergencies or obvious conditions and determining whether there is a significant “ear-related” component.
2) Causes from a neurological perspective (brain, auditory pathways, neuroplasticity)
Neurologic, tinnitus is not “just sound,” but can be seen as a pathological activation of neural networks from the auditory system and related areas.
Modern Neurological Mechanisms Explained Simply:
after hearing loss (even if slight) the brain tries to “fill in the lack of signal”
changes occur in the auditory nuclei and auditory cortex
increase “background noise” (hyperexcitability, abnormal synchronization)
result: phantom sound guess perceived as real
This concept is supported by neuroscience literature on maladaptive plasticity and the “tinnitus loop”.
3) Imaging: When and Why We Investigate Tinnitus with MRI/CT/Doppler
Imaging is not the “first line of treatment” for all cases of tinnitus, but it becomes essential in certain situations:
✅ Cerebral MRI / Cerebellopontine angle (especially for unilateral tinnitus + hearing loss + neurological symptoms)
✅ MRI Angiography / Doppler if tinnitus is pulsatile (in sync with the pulse)
✅ CT temporal in certain ENT structural causes
Imaging is particularly useful for:
ruling out rare but serious causes
vascular or structural mechanisms orientation
establishing a complete patient map before complex therapy
4) Rheumatology / Orthopedics / Rehabilitation: The Role of the Cervical Spine, Posture, and Myofascial Chains
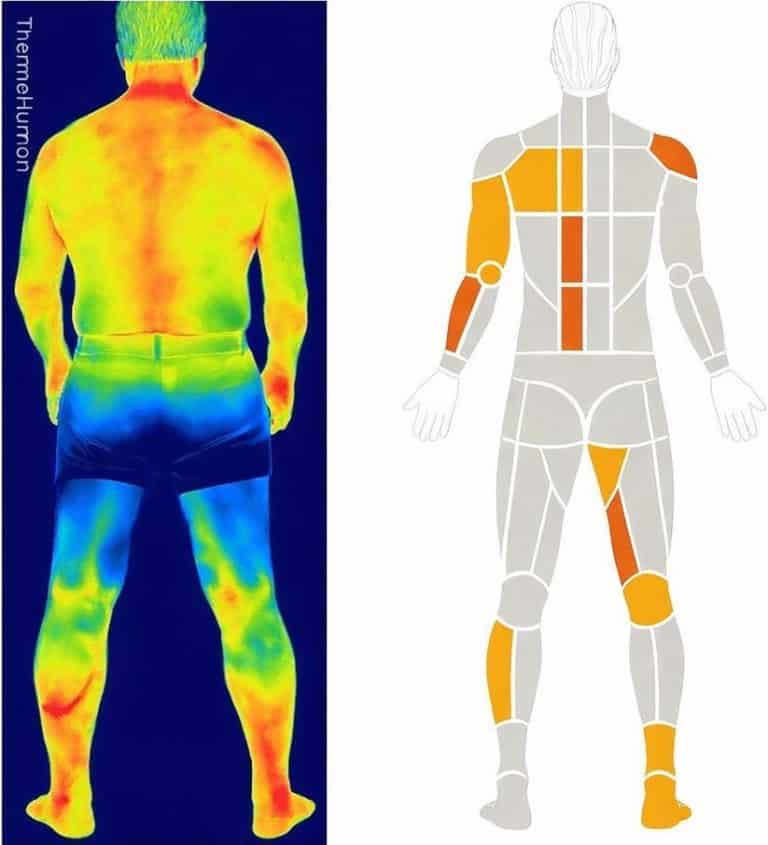
From an orthopedic and functional perspective, tinnitus can be somatic modulation to:
cervical tension (C1–C3)
SCM, trapezius, suboccipitals trigger points
postural dysfunctions (rounded shoulders, forward head posture)
Thoracic stiffness and myofascial chain imbalances
In many cases, the patient notices that the tinnitus:
It intensifies with stress, fatigue, and poor posture.
changes to neck / jaw movements
These signs are extremely important for the diagnosis of somatosensory tinnitus.
5) Psychology / Psychiatry: “Why tinnitus gets louder when you’re anxious”
An essential clinical fact:
Tinnitus is not just an auditory sensation; it is also an emotional experience.
The brain can “amplify” tinnitus by:
hypervigilance (constant focus on sound)
anticipatory anxiety (“I'll never get away with this”)
Insomnia and chronic fatigue
Limbic reaction (sound perceived as a threat)
Tinnitus thus enters a vicious cycle:
sound → stress → tension → neurological hyperactivation → louder sound.
The TMJ Connection: Why the Temporomandibular Joint Can Cause Tinnitus
What is the ATM and why is it relevant for the ear?
Temporomandibular joint (TMJ) This is the joint between the mandibular condyle and the temporal bone. It is one of the most complex joints in the body: it combines rotation + translation is controlled by strong muscles and is directly influenced by:
occlusion
bruxism
stress
cervical posture
left-right bilateral balance
Anatomically, the ATM is in close proximity to the structures of the ear, and functionally it is part of an ecosystem called Stomatognathic system.
Prevalence and frequency: how often does tinnitus occur in TMJ dysfunction?
Recent studies show that:
Tinnitus can appear significantly more frequently in patients with TMD (temporomandibular joint dysfunction)Taylor & Francis Online)
in a 2025 analysis, the prevalence of tinnitus in patients with TMD was reported at around 30%, especially in association with masseter pain and TMJ osteoarthritis (PMC)
So, Tinnitus + TMJ pain / jaw clicking / bruxism / limited mouth opening / deviation it must be viewed as a serious clinical combination, not as a coincidence.
Key Mechanism: Somatosensory Tinnitus (TMJ + Cervical)
In a subpopulation of patients, tinnitus can be jaw or neck movements through somatosensory-auditory interactionsPubMed).
In other words:
Muscular/articular input (TMJ, neck) can enter the auditory circuit
the brain can translate it as sound or intensify existing sound
This is the basis for what we call today:
✅ Tinnitus of TMJ origin
✅ Cervico-mandibular tinnitus
✅ tinnitus somatic / somatosensory
Tinnitus with low vs. high frequencies: what can the signals suggest?
Although each patient is different, there are some useful guidelines:
Tinnitus high pitch (whistle)
Most commonly associated with:
high-frequency hearing loss
chronic noise / headphones
Central mechanism (neuroplasticity)
The majority of patients “match” their tinnitus to over 3 kHzPMC)
Tinnitus with (low pitch: “humming / vibration”)
May appear in:
Meniere's (typical 125–250 Hz) (PMC)
Fluctuating vestibular mechanism
somatosensory (TMJ/cervical) in certain clinical profiles
What aggravates tinnitus when the cause is TMJ (and what can “relax” it)?
Atm factors that worsen tinnitus:
nocturnal bruxism
Masseter/pterygoid tension
Temporomandibular joint inflammation
unstable occlusion (premature contacts)
mandibular deviation / muscular asymmetry
Compensatory cervical posture
Temporomandibular joint (TMJ) tinnitus: what can predictably relieve it
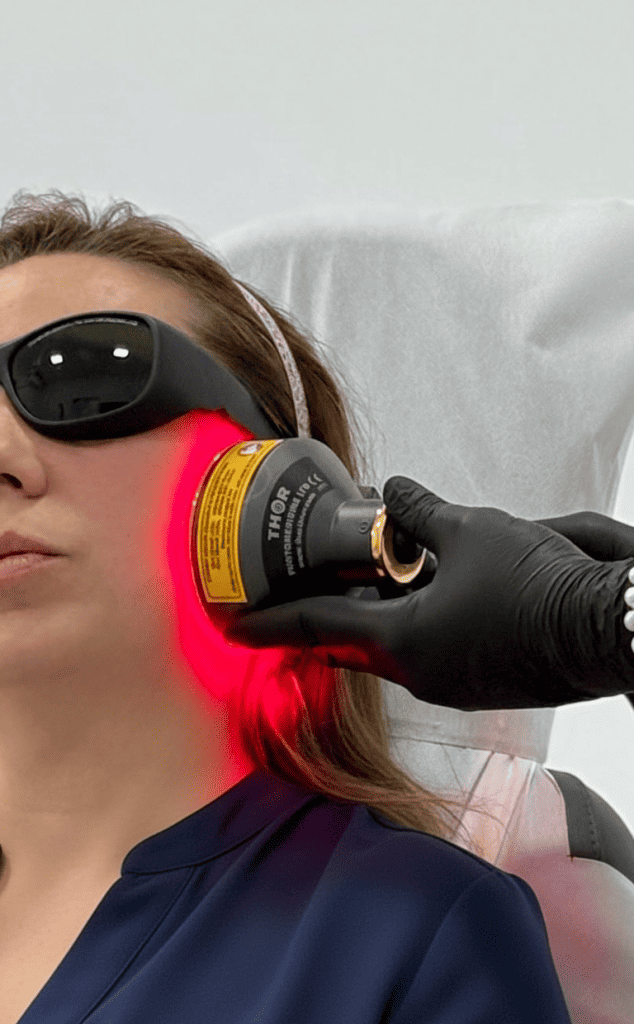
Muscle relaxation (laser therapy)
functional adjustment of the jaw position
left-right bite force balancing
Reducing neurovegetative hyperactivity
Occlusal stabilization with a custom occlusal splint (when indicated)
Many patients say:
“It eases up when I relax my jaw”
sau
“It gets worse after a stressful day when I clench my teeth.
These phrases are almost diagnostic.
The brain and the “sound map”: why tinnitus isn't just treated locally
There is a very important idea in the literature:
the auditory system is not just the ear, but also auditory cortex where there is a tonotopic map (organize by frequencies, like a “keyboard”). In tinnitus, this map can become distorted, and the brain can produce a persistent signal even in the absence of an external source.
This concept is related to:
maladaptive neuroplasticityPMC)
central networks (attention, limbic, auditory memory)PMC)
Connections between the auditory and somatosensory systems (ATM/cervical)Document Server)
Therefore, the modern approach clearly states:
✅ Tinnitus requires multidisciplinary treatment.
FAQs – Frequently Asked Questions about Tinnitus and TMJ
Yes, in some patients, tinnitus is predominant somatosensory (TMJ/cervical). Studies show significant associations between TMJ dysfunction and tinnitus.Taylor & Francis Online).
This is a very suggestive sign. There are clear descriptions of tinnitus modifiable by mandibular/cervical movements through somatosensory-auditory interactions (PubMed).
Yes. Bruxism overloads the masseter and pterygoid muscles, the TMJ, and can accentuate somatic input to the auditory system.
Besides ENT and audiogram, the following are useful:
evaluate functional clinical ATM
Facial and axial (postural) thermography
Left-right bite force analysis
intraoral scan
TMJ ultrasound
sometimes MRI TMJ / MRI brain (depending on the case)
Stress can amplify tinnitus, especially through neuro-psychic mechanisms, but most of the time there is also a functional (TMJ/cervical) or auditory substrate that is worth investigating.
In conditions where the cause is muscular/articular (TMJ) and there is a somatosensory component, laser therapy can be a very valuable method for:
pain and tension relief
reducing inflammation
peripheral neuromodulation
It depends on the age and severity. In many cases, it's done in stages:
early anti-inflammatory/relaxation phase
functional stabilization phase
prevention phase (occlusion, posture, bruxism)
Sometimes yes, other times it can be significantly reduced in intensity and impact. The key is identifying the correct type: auditory vs. somatosensory vs. mixed.
Somatosensory tinnitus requires multidisciplinary treatment. At Innovation Medical Center, we combine functional diagnostics with laser technology to offer a modern and effective therapeutic approach.
Schedule a comprehensive evaluation
📍 București – www.innovationmedical.ro
📞 0753 666 111
Autor: Dr. Anca Adam, Medic Specialist in Medicina Fizica si de Reabilitare, compartiment recuperare neurologică și disfuncții ATM/TMJ, Expert Acupunctură Laser & Competenta Medicina Traditionala Chineza (Tai Yuan China), Termografie Medicală (Barcelona, Spania) – LSO (Laser Safety Officer) AALZ Aachen Germania.





























 Romanian
 English